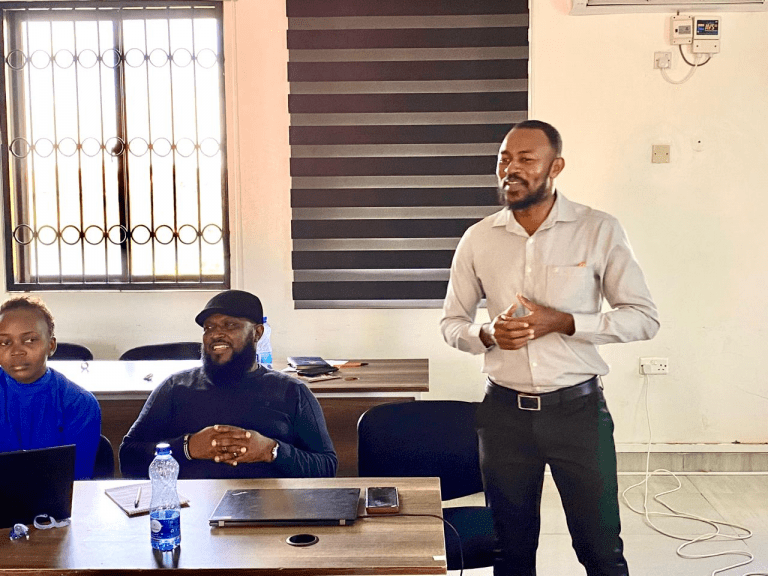
By Shadrack Babu, Research Associate
At the 16th KASH Conference hosted by KEMRI (10–13 February 2026), Shadrack Babu, Research Associate at Global Health Innovations – Kenya, presented a compelling case series titled:
“Examining Mother-to-Child Transmission of HIV: A Case Series of 8 Mother–Infant Pairs Enrolled in PMTCT Services.”
The findings offer important insights into how pediatric HIV infections continue to occur, even within strong national prevention programs.
 Mother-to-child transmission (MTCT) of HIV can occur during pregnancy, delivery, or breastfeeding. Globally, MTCT accounts for over 95% of pediatric HIV infections, with the highest burden concentrated in low- and middle-income countries.
Kenya has made remarkable progress toward elimination of MTCT (eMTCT), aligning with WHO’s global plan and implementing a robust “test-and-treat” strategy that includes:
While these interventions have positioned Kenya as a regional leader in PMCT, pediatric HIV infections are on the rise with national reports indicating a 9.3%
And yet, approximately 5,200 pediatric HIV infections are still recorded annually.
This raises a critical question: Where are the gaps?
This study examined the treatment pathways of eight mother–infant pairs enrolled in PMTCT and Early Infant Diagnosis (EID) services where HIV transmission still occurred.
The goal was straightforward but vital:
Identify patterns, missed opportunities, and system gaps that may have contributed to transmission — despite program coverage.
This was a descriptive case series nested within the HITSystem 2.1-A PMTCT viral load monitoring study (2020–2024), implemented across 12 hospitals in Kenya, spanning Coast and Kisumu regions.
Infant HIV status was confirmed through routine Early Infant Diagnosis (EID) in line with Ministry of Health guidelines.
Data abstraction included:
– Timing of antenatal care (ANC) enrollment
– ART initiation status
– Viral load testing history
– Delivery mode
– Infant prophylaxis and testing timelines
Descriptive analysis was used to trace care cascades and identify breakdown points.
Out of 1,394 infants enrolled in the parent study:
– 8 infants (0.57%) were diagnosed HIV-positive.
– Mean maternal age: 28.7 years
– Mean gestational age at ANC enrollment: 25.6 weeks
– Mean infant age at first HIV test: 12.3 weeks
– All infants had documented prophylaxis
On the surface, these indicators suggest engagement in care.
But deeper analysis revealed something more important: Transmission occurred despite contact with services.
All eight cases demonstrated gaps along the PMTCT cascade. Key themes included:
Early ANC enrollment and timely ART initiation are critical. Late presentation reduces the window for viral suppression before delivery.
Routine and uninterrupted viral load testing is essential to identify high-risk mothers and intervene promptly. Missed or delayed VL tests represent lost opportunities to prevent transmission.
Male partner involvement, disclosure dynamics, and broader social support influence adherence and continuity of care. Where these were weak, risks increased.
– Gaps in continuity across facilities
– Delivery outside recommended facility settings
– Supply chain vulnerabilities
These are not isolated failures, they are system-level friction points.
The central takeaway from this case series is powerful:
Elimination of mother-to-child transmission (eMTCT) is not just a clinical goal. It is a systems-strengthening effort.
High national coverage does not automatically translate into universal protection. Sustained engagement is required throughout:
– Pregnancy
– Delivery
– Postpartum
– Breastfeeding
Strengthening PMTCT programs must therefore include:
– Incentivizing and supporting early ANC enrollment
– Ensuring uninterrupted viral load monitoring
– Enhancing male partner engagement and community health volunteer (CHV) involvement
– Reinforcing supply chains and service continuity
Kenya is close to eliminating MTCT — but “close” is not the same as “complete.”
Each pediatric infection represents:
– A preventable transmission
– A signal of a system gap
– An opportunity to refine programs
By examining real-world cases where transmission occurred despite service availability, this research provides actionable insights to move from progress to precision.
At Global Health Innovations – Kenya, our commitment is clear: we must not only scale services — we must strengthen pathways.
Elimination is possible. But it requires vigilance, systems thinking, and sustained investment in both clinical excellence and program delivery.